A child who has been dry for months or years and suddenly starts having wet nights can leave parents with questions – and children with worries they may not know how to voice. Bedwetting after being dry at night is more common than many families realise. It is not laziness, attention-seeking or a sign that your child has done something wrong. It is a change worth noticing with kindness, practical support and, sometimes, medical advice.
The first priority is preserving confidence. A wet bed is inconvenient, but it should never become a source of shame. Calm reassurance, discreet protection and a straightforward plan can make a difficult patch feel much more manageable.
What does bedwetting after being dry at night mean?
Healthcare professionals often describe a return to bedwetting after at least six months of dry nights as secondary nocturnal enuresis. The word may sound clinical, but it simply gives a name to a pattern: a child has previously developed night-time bladder control, then begins wetting the bed again.
One or two isolated wet nights do not necessarily mean there is a problem. Children can wet the bed when they are unusually tired, unwell or sleeping away from home. If wetting becomes regular, however, or arrives alongside changes in daytime toileting, thirst, mood or health, it is sensible to look more closely.
Night-time dryness relies on several systems working together. The bladder needs to hold urine comfortably, the body needs to make less urine overnight, and the brain needs to respond to a full bladder by waking or holding on. A disruption in any part of that process can lead to wet nights.
Common reasons wet nights can return
Sometimes there is a clear trigger; often there is not. The most useful approach is curiosity rather than blame.
Constipation can affect the bladder
Constipation is a very common and easily missed contributor to bedwetting. A full bowel can press on the bladder, reducing the amount it can hold and making bladder signals harder to manage. Your child may still be opening their bowels regularly and be constipated, particularly if stools are hard, painful, infrequent or very large.
If constipation is suspected, speak to a pharmacist, GP or continence professional rather than trying to solve persistent symptoms alone. Treating it properly can make a meaningful difference to both daytime and night-time bladder control.
A urine infection or another health concern
A urinary tract infection can cause new wetting, as well as pain or stinging when passing urine, needing the toilet more often, tummy pain, fever or urine that looks or smells unusual. Contact your GP promptly if these symptoms are present.
Book a GP appointment sooner rather than later if your child is suddenly very thirsty, passing much more urine than usual, losing weight, feeling unusually tired, or becoming unwell. These signs need assessment to rule out conditions such as diabetes. New snoring, restless sleep or breathing pauses can also affect sleep and bedwetting, so mention these too.
Stress, change and big feelings
Starting a new school, family separation, bereavement, bullying, moving house or a new baby can unsettle a child’s sleep and toileting patterns. Stress is not always the sole cause, and it should not be assumed that wetting is ‘all in their head’. But emotional pressure can make an existing vulnerability more visible.
A gentle conversation may help. Choose a neutral moment, not the middle of a wet-night clean-up, and make space for feelings without demanding an explanation. Some children will have a clear concern to share; others simply need to hear that they are safe and not in trouble.
Daytime bladder habits
Holding on for long periods, rushing to the toilet, frequent small wees, urgency or daytime accidents can point to a bladder that needs support during the day as well as at night. Children may avoid school toilets because they are busy, lack privacy or feel unpleasant. Regular, relaxed toilet visits and enough fluid spread through the day can help establish better habits.
Try not to respond by drastically restricting drinks. Children need adequate daytime hydration. It is usually more helpful to encourage most drinks earlier in the day, reduce caffeinated or fizzy drinks where relevant, and keep the last part of the evening calm and predictable.
When to contact a GP
It is reasonable to contact your GP if bedwetting returns after six months or more of dryness, especially if it happens repeatedly. A GP can ask about bowel habits, daytime symptoms, sleep, emotional wellbeing, medicines and family history, and may check a urine sample.
Seek more urgent advice if bedwetting is accompanied by pain when weeing, fever, blood in the urine, severe tummy or back pain, extreme thirst, weight loss, vomiting, marked tiredness, weakness in the legs, or new problems controlling bowels. These symptoms do not automatically mean something serious, but they should not be left to wait.
A medical check is not about making bedwetting feel more alarming. It is about making sure your child gets the right support, particularly when a previously dry child has a noticeable change in their pattern.
What helps at home while you find the cause
The practical work of wet nights can quickly become exhausting. A plan that protects bedding and protects dignity can reduce the disruption for everyone.
Keep your response low-key. Help your child change into dry clothes if needed, use waterproof bedding protection, and avoid discussions that sound like disappointment. Some families find it useful to prepare clean pyjamas and a towel or spare sheet within easy reach, so a child can take part in the routine without feeling exposed.
Reusable absorbent sleepwear can offer discreet protection for tonight, particularly for sleepovers, school trips, holidays or periods when a child is anxious about leaks. It will not treat the cause of bedwetting, but it can reduce laundry, protect the mattress and give a child more confidence while you address the bigger picture. The right option depends on the volume of wetting, your child’s comfort and whether they want to manage changing independently.
Avoid lifting a sleeping child to the toilet as a long-term solution. It may keep the bed dry temporarily, but it does not usually help them learn to recognise and respond to their own bladder signals. Likewise, reward charts can be discouraging when they reward dry nights alone, because a child cannot fully control whether they wake. If you use encouragement, praise helpful actions instead: drinking well during the day, using the toilet before bed, putting on protective sleepwear or helping calmly after an accident.
Can an alarm help a child become dry again?
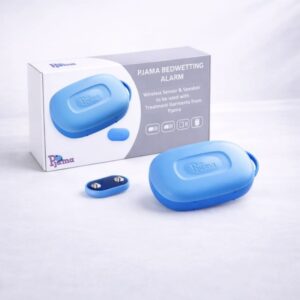
For children with regular bedwetting, an alarm is one of the main evidence-based treatments for achieving lasting dry nights. The sensor detects the first drops of urine and sounds an alarm, helping the child gradually learn to wake to a full bladder or hold on until morning.
Alarm treatment requires consistency, and the first few weeks can be demanding. Many children sleep through the sound at first, so a parent or carer may need to wake with them, guide them to the toilet, reset the alarm and record progress. It is not the best fit for every family at every moment – for example, during an acute illness, a major family crisis or when everyone is already severely sleep-deprived.
When the timing is right, a structured programme gives families a clearer route than simply waiting and hoping. Systems such as Pjama DryGuardians combine a clinically tested alarm with sensor-compatible underwear, parent support through an app and progress tracking, helping families stay consistent and see patterns over time. If your child has new daytime symptoms or possible constipation, seek clinical advice alongside treatment rather than relying on an alarm alone.
Supporting confidence beyond the bedroom
Children often worry less about the wet bed itself than about who might find out. Sleepovers, camps and school residential trips can feel impossible when bedwetting returns. Offer choices wherever you can: whether to use protective sleepwear, who should know, how to pack a discreet bag, and what words to use if help is needed.
You might say, “Lots of children need extra night-time protection for a while. We can make a plan that lets you still go.” That message matters. It separates the condition from the child and keeps friendships, travel and independence within reach.
Progress is rarely perfectly straight. There may be dry nights, then a setback during illness or a busy week at school. Keep the focus on comfort, information and steady support. With the right assessment, practical protection and a treatment plan when appropriate, wet nights do not have to limit your child’s confidence or their place in family life.